
Introduction
The diagnostic approach to constipation must be selective, targeted, and stepwise, avoiding both the underutilization and the indiscriminate use of tests. Diagnostic investigations are not intended to “confirm” constipation, but rather to identify its underlying mechanism, differentiate pathophysiological subtypes, and guide specific therapeutic decisions.
In patients with persistent constipation despite initial measures, functional evaluation makes it possible to distinguish between alterations in colonic transit, defecatory disorders, or combinations of both – scenarios that require clearly differentiated therapeutic strategies.
Before requesting any test for the investigation of constipation, three fundamental prerequisites must be met:
- –There must be a specific clinical question (slow transit? defecatory disorder? sensory dysfunction?).
- –Is there a failure of or a suboptimal response to initial treatment?
- Tests are primarily indicated in refractory constipation.
- –Can the test modify therapeutic management?
A test that does not change clinical management has no clinical utility.
The diagnosis of chronic constipation should be based on a detailed medical history and a thorough physical examination, with special emphasis on dynamic digital rectal examination. Furthermore, it is essential to confirm that the patient has received appropriate initial therapeutic management, including dietary modifications, increased physical activity, use of fiber when indicated, and treatment with osmotic laxatives.1
Refractory constipation must meet the following criteria:2
- –The patient must satisfy diagnostic criteria for chronic constipation or constipation-predominant irritable bowel syndrome.
- –Persistence of symptoms despite appropriate management with dietary and lifestyle measures, adequate use of over-the-counter laxatives, and approved pharmacological treatments when indicated.
- –Presence of one or more of the following clinical features: fewer than three complete bowel movements per week, persistent or progressive straining, absence of improvement in stool consistency (Bristol < 3) despite treatment, insufficient clinical improvement from the patient’s perspective, or intolerance or adverse effects rendering treatment unacceptable.
The absence of response to these measures and refractory constipation – defined as the persistence of infrequent evacuations or unsatisfactory defecation, with or without abdominal pain, despite appropriate treatment2 – constitute the clinical criteria for initiating physiological evaluation.
Importance of pathophysiological characterization
Various studies have demonstrated that up to 40% of patients with chronic constipation present with a defecatory disorder, primarily dyssynergic defecation. This condition may coexist with slow colonic transit or induce it secondarily through rectocolonic inhibitory reflexes, generating a significant overlap between both phenotypes.1 Refractory constipation is not a homogeneous condition; rather, it results from distinct pathophysiological mechanisms including altered colonic transit, rectal evacuation disorders, and, in some cases, multiregional gastrointestinal dysmotility. Therefore, the diagnostic evaluation must follow a structured sequence that allows for the identification of evacuatory disorders before attributing symptoms to a primary colonic dysfunction.
Motility studies
Approximately 35-40% of patients with chronic constipation evaluated by anorectal tests present with an undiagnosed and inadequately treated defecatory disorder.3 This is defined by the presence of constipation associated with ineffective rectal evacuation, secondary to insufficient rectal propulsive force, inadequate anal relaxation, or both. For the specific evaluation of colonic and anorectal function, the most widely used methods are anorectal manometry and the study of colonic transit time.4
Anorectal manometry and balloon expulsion test
Anorectal manometry combined with the balloon expulsion test is generally sufficient to establish the diagnosis of a defecatory disorder and constitutes the cornerstone of its management. Moreover, these tests allow prediction of which patients will benefit from biofeedback, optimizing the use of therapeutic resources.
Anorectal manometry evaluates anal tone at rest and during voluntary contraction, the reflex motor response of the external anal sphincter with the cough maneuver, rectoanal coordination during defecatory effort, the generation of rectal propulsive force and the degree of anal sphincter relaxation, rectal sensitivity, and the integrity of the rectoanal inhibitory reflex.5 From these measurements, the rectoanal gradient is calculated, which may be reduced or negative during defecatory effort. The most relevant findings for identifying a defecatory disorder are a reduced or negative rectoanal gradient during straining, a prolonged balloon expulsion test (> 1 minute), and incomplete evacuation on defecography. Other frequently associated findings include elevated resting pressure (anismus) and insufficient anal relaxation during effort.
Although high-resolution anorectal manometry offers a spatial characterization of anorectal pressures, the rectoanal gradient may be negative even in asymptomatic subjects, which limits its diagnostic value in isolation. This information is essential for identifying patterns of dyssynergic defecation, anismus, or sensory alterations; however, manometry does not fully reproduce physiological defecation, and its interpretation depends largely on the examiner’s experience. Therefore, it should not be considered a standalone test but should be complemented by a balloon expulsion test.6 The latter is one of the most useful and practical tests for screening evacuatory dysfunction. It consists of placing a balloon in the rectum, which is inflated with 50 ml of water, and the patient is asked to go to the toilet and attempt to expel it. The result is considered normal when expulsion occurs in less than 1 minute, whereas a longer time suggests an alteration of the defecatory mechanism. Its simplicity, low cost, and good correlation with dyssynergic defecation account for its widespread use in clinical practice, even in resource-limited settings. However, the balloon expulsion test does not identify the underlying pathophysiological mechanism and may be normal in a subset of patients with defecatory disorders, reinforcing the need for a combined interpretation with other tests.7
The diagnosis of a defecatory disorder is established when at least two of three tests are abnormal: anorectal manometry, the balloon expulsion test, or defecography. In patients with findings compatible with a defecatory disorder associated with alterations in rectoanal coordination, treatment through pelvic floor biofeedback represents the therapeutic intervention of choice, with response rates superior to those observed with pharmacological treatment alone.8 Normalization of the balloon expulsion test following therapy constitutes an objective marker of resolution of the evacuatory disorder. A meta-analysis reported that 50% of patients with chronic constipation have dyssynergic defecation according to anorectal manometry,9 compared with 60% of patients with dyssynergic defecation and a delayed colonic transit time, which may be secondary to the evacuatory disorder.10 Colonic transit may accelerate, and symptoms may improve or even resolve with treatment of the evacuatory disorder.11,12 Therefore, slow colonic transit in isolation does not reflect colonic inertia and does not imply a colonic motility disorder as the sole cause of constipation.
Assessment of colonic transit
Colonic transit studies – including radiopaque markers, colonic scintigraphy, and the wireless motility capsule – are considered second-line physiological tools in the evaluation of functional constipation in adults. Their use is not systematic in the initial phases; rather, it becomes necessary in specific clinical contexts, primarily in patients with refractory constipation following adequate evaluation and treatment of the anorectal compartment.13 In this context, the determination of colonic transit allows differentiation between normal-transit constipation and slow-transit constipation, information that is essential for guiding subsequent therapeutic decisions. Confirmation of slow transit may justify intensification of pharmacological treatment through more aggressive strategies, such as the combined use of secretagogues, high-dose stimulants, or prokinetic agents used off-label, whereas normal transit necessitates reconsidering alternative mechanisms responsible for symptoms and limits the indication for invasive interventions (Fig. 1).
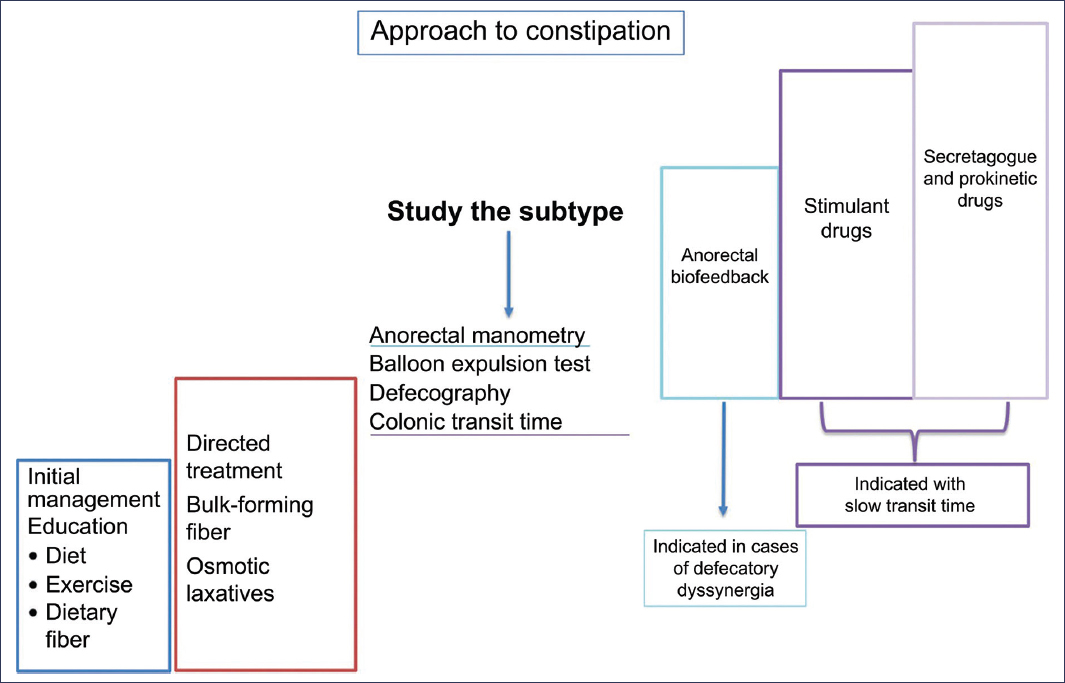
Figure 1. The treatment of constipation is stepwise: it begins with education, dietary changes, exercise, and increased fiber intake; if the response is insufficient, bulk-forming fiber and osmotic laxatives are added. In the event of therapeutic failure, the pathophysiological subtype is characterized through functional studies. Treatment is individualized according to findings: biofeedback for dyssynergic defecation, and stimulant laxatives, secretagogues, or prokinetics for slow-transit constipation.
A second key indication corresponds to patients whose symptoms persist following effective treatment of the defecatory disorder, particularly after biofeedback rehabilitation, or to those in whom such a disorder has been reasonably excluded through appropriate physiological tests.3,13 The specialized literature emphasizes that colonic transit studies should only be performed during this post-anorectal evaluation phase, with the aim of identifying a possible coexisting slow transit that explains the persistence of symptoms.
Colonic transit studies are also indispensable in the preoperative decision-making process, particularly before considering subtotal colectomy or neuromodulation therapies. Various international consensus statements and subsequent analyses agree that objective demonstration of markedly delayed colonic transit constitutes an indispensable requirement before surgery, whereas the presence of normal transit represents an absolute or near-absolute contraindication.3 Recent studies have demonstrated that, when applying strict selection criteria based on colonic transit and anorectal function, only a minority of patients with refractory constipation truly fulfill the criteria for colectomy, with the majority being excluded due to normal gastrointestinal transit or concomitant sphincter dysfunction.
The objective of colonic transit assessment is to characterize the motor function of the colon and to differentiate between normal-transit constipation, slow-transit constipation, and mixed forms.3,4,15
Available methods for evaluating colonic transit time include the radiopaque marker study, colonic scintigraphy, and the wireless motility capsule, which provides a more comprehensive view of gastrointestinal transit, enabling segmental assessment of gastric emptying, intestinal transit, and colonic transit within a single study. Its primary utility is in patients with suspected generalized motor disorders or overlapping symptoms, such as abdominal distension, dyspepsia, and constipation. However, its high cost and limited availability, as well as its still-controversial therapeutic impact, restrict its use to selected cases.3,4,15 The radiopaque marker study is the most widely used in clinical practice owing to its broad availability, low cost, and good capacity to discriminate between normal and delayed transit, as well as to identify patterns of diffuse or distal retention.16 Colonic transit time is assessed through ingestion of radiopaque markers using single or serial ingestion protocols. In the serial method, the patient ingests one capsule containing 20 markers daily for three consecutive days, and a plain abdominal X-ray is obtained on days four and seven. The total number of retained markers allows estimation of the global colonic transit time; retention of ≤ 20 markers is considered normal. The segmental distribution of markers – right colon, left colon, and rectosigmoid – is used to identify patterns of normal transit, slow colonic transit, or distal retention suggestive of a defecatory disorder.17
For correct interpretation, patients should discontinue laxatives at least 7 days before the study and drugs that slow colonic transit for 2 weeks.15 Nevertheless, intraindividual reproducibility is limited, especially in patients with defecatory disorders or colonic inertia, so repetition of the study may be necessary, even during laxative use.17
There is significant overlap (up to 40%) between slow transit and defecatory disorder, probably mediated by rectocolonic inhibitory reflexes secondary to distal fecal retention.3 Normal colonic transit while on laxative treatment suggests that symptoms may be attributable to a defecatory disorder, visceral hypersensitivity, or treatment-related adverse effects, whereas persistently slow transit points to primary colonic dysmotility.
Utility of defecography in constipation
Anatomical abnormalities of the anorectal compartment, such as large rectoceles or rectal mucosal prolapse, may be associated with distal constipation by mechanically interfering with the evacuatory process. Both dyssynergic defecation and these structural anomalies constitute distinct pathophysiological conditions that require specific therapeutic approaches; therefore, their identification is a priority before undertaking an exhaustive evaluation of colonic motility. It should be noted that clinical semiology has a limited discriminative capacity for differentiating between the various subtypes of constipation; in this regard, the sensation of incomplete evacuation has been described as a nonspecific symptom that may derive both from alterations in defecatory coordination and from anatomical defects of the pelvic floor, including large rectoceles and mucosal prolapse. Defecography constitutes a complementary tool within the diagnostic algorithm, but not a first-line study.8,13 It does not replace manometry, but rather fulfills a specific role in selected scenarios where manometric information is insufficient or incomplete to establish the definitive diagnosis.2
One of the principal indications for defecography is the evaluation of patients with symptoms suggestive of evacuatory obstruction – such as excessive straining, a sense of anal blockage, incomplete evacuation, or the need for digital maneuvers – when findings from anorectal manometry and the balloon expulsion test are discordant, borderline, or inconclusive.18 In these circumstances, defecography allows direct visualization of the evacuatory process, providing dynamic information that cannot be obtained through static functional tests.13
Likewise, defecography is particularly indicated when dynamic anatomical abnormalities of the posterior pelvic compartment are suspected; these include clinically significant rectocele, rectorectal or rectoanal intussusception, enterocele, excessive perineal descent, and internal or external rectal prolapse.13,18 These conditions cannot be adequately diagnosed by anorectal manometry and require imaging studies during defecatory effort for their identification and functional characterization.20
From a diagnostic standpoint, numerous reviews focused on defecatory disorders establish that pathophysiological diagnosis requires the coexistence of compatible symptoms, manometric alterations, and at least one additional abnormal test, which may be the balloon expulsion test, defecography, or demonstration of distal retention on colonic transit studies.4,8,21 On occasion, defecography may be used as a confirmatory test when diagnostic uncertainty exists or when a more complete evaluation of the evacuatory mechanism is required.
Another relevant indication for defecography is the preoperative evaluation of patients who are candidates for pelvic or colorectal surgery. Guidelines emphasize that, prior to any intervention aimed at correcting defecatory obstruction – such as rectocele or prolapse surgery – it is essential to precisely document the functional anatomy and the coexistence of multiple pelvic floor defects.15,21 Defecography plays a central role in this context, as it allows identification of combined abnormalities that could influence the surgical outcome and prevent inappropriate procedures.
It is important to note that defecography should not be requested systematically or as part of the initial evaluation of chronic constipation. Available evidence demonstrates that a significant proportion of patients with defecatory disorders present with secondary slow colonic transit, which may normalize following biofeedback treatment.2,8,20 For this reason, the early performance of imaging or transit studies without a prior anorectal evaluation may lead to erroneous interpretations and inappropriate therapeutic decisions.
Defecography should be reserved for well-defined clinical situations: suspicion of dynamic structural pathology, inconclusive results from manometry and the balloon expulsion test, need for diagnostic confirmation of a defecatory disorder, or preoperative evaluation before pelvic or colorectal surgery.1,8,13,18–20 Its indiscriminate use does not increase diagnostic yield and may increase costs, radiation exposure, and the detection of incidental findings of no clear clinical relevance.
In summary, defecography is indicated when direct evaluation of evacuation is required to clarify the etiology of defecatory symptoms, especially in the context of inconclusive or discordant results from other diagnostic modalities, or when structural abnormalities of the pelvic floor are suspected. It constitutes a complementary second-line study within the contemporary approach to chronic constipation. Its indication must be individualized and always integrated into a stepwise diagnostic algorithm that prioritizes anorectal functional evaluation. When used in the appropriate context, it provides anatomical and dynamic information of high clinical value; outside of that context, its diagnostic yield is limited and potentially confusing.
Conclusions
Chronic constipation is a complex and heterogeneous clinical syndrome whose adequate diagnostic evaluation demands a structured, stepwise pathophysiological approach. Diagnostic tests should not be used indiscriminately or for merely descriptive purposes, but rather as tools directed at identifying the predominant pathophysiological mechanism responsible for symptoms and at guiding therapeutic decisions with genuine clinical impact. A substantial proportion of patients with chronic constipation present with defecatory disorders that are often unrecognized during the initial evaluation and potentially reversible through specific therapies, such as biofeedback. For this reason, functional characterization of the anorectal compartment through anorectal manometry and the balloon expulsion test constitutes the initial pillar of physiological evaluation in refractory constipation and must precede the interpretation of colonic transit studies.
Colonic transit studies, in turn, play a fundamental role as second-line tools, particularly in patients with persistent symptoms after exclusion or adequate treatment of evacuatory disorders, or in the context of advanced therapeutic decisions, such as pharmacological intensification or consideration of surgical interventions. Objective demonstration of markedly delayed colonic transit is indispensable before any invasive strategy, whereas the presence of normal transit necessitates reconsidering the origin of symptoms and limits the indication for irreversible procedures.
Defecography complements the functional evaluation in selected scenarios, especially when dynamic anatomical abnormalities are suspected or when manometric findings are inconclusive. Its value resides in its capacity to integrate anatomical and functional information during evacuation, thereby contributing to a more precise therapeutic selection and appropriate surgical planning.
Taken together, the value of diagnostic tests in constipation lies not in their number or technological sophistication, but in their correct indication, integrated interpretation, and clinical application. A rational approach, centered on pathophysiology and oriented toward modifying therapeutic management, allows optimization of outcomes, avoidance of unnecessary interventions, and significant improvement in the quality of life of patients with refractory chronic constipation.
Funding
The author declares that no funding was received for this study.
Conflicts of interest
The author declares no conflicts of interest.
Ethical considerations
Protection of persons and animals. The author declares that no experiments were performed on human beings or animals for this research.
Confidentiality, informed consent, and ethical approval. The study does not involve personal data, medical records, or human biological samples; therefore, it does not require ethical approval. The SAGER guidelines do not apply.
Statement on the use of artificial intelligence. The author declares that no generative artificial intelligence of any kind was used for the writing or creation of content in this manuscript.
