Neurophysiological mechanisms of defecation
Primary chronic constipation is commonly associated with abnormalities in intestinal movements or dysfunction of coordinated pelvic floor muscle contraction during defecation. The motor activity that supports propulsive motility throughout most of the gastrointestinal tract is peristalsis, which involves coordinated contraction and relaxation of the intestinal muscle layer, resulting in a pressure gradient that propels luminal content through the intestine. Although peristalsis occurs in the colon, it is not the primary mechanism of propulsion. Instead, colonic propulsion leading to defecation is driven mainly by high-amplitude propagated contractions (mass movements) that occur several times per day.1–3
Peristalsis can be activated by chemical or mechanical stimuli detected by enteroendocrine cells, such as enterochromaffin cells, or by mechanosensitive neurons in the enteric ganglia. Enterochromaffin cells synthesize and release serotonin 5-hydroxytryptamine (5-HT) in response to nutrients, bile salts, short-chain fatty acids, and mechanical stimuli. 5-HT can activate serotonergic receptors on primary afferent neurons, which transmit signals through interneurons along the myenteric plexus to selectively activate excitatory motor neurons and diminish the activation of inhibitory motor neurons. Excitatory motor neurons primarily trigger smooth muscle cell contraction through the release of acetylcholine, whereas inhibitory motor neurons cause smooth muscle cell relaxation through purinergic (adenosine triphosphate) and nitrergic (i.e., nitric oxide) factors.3
Interstitial cells play a role in mediating excitatory and inhibitory signals between the enteric nervous system and smooth muscle cells. Two cell types of interstitial cells, the interstitial cells of Cajal and the platelet-derived growth factor receptor alpha cells, contribute to syncytial connection networks with smooth muscle cells. The interstitial cells of Cajal, which also serve as pacemaker cells that initiate slow-wave action potentials in gastrointestinal smooth muscle cells, receive cholinergic synaptic inputs from excitatory motor neurons and nitrergic inputs from inhibitory motor neurons. Excitatory and inhibitory inputs lead to increases in frequency and decreases in amplitude of slow-wave potentials, resulting in increases or decreases in muscle tone. Activation of purinergic receptors on platelet-derived growth factor receptor alpha cells leads to hyperpolarization that spreads to smooth muscle cells and inhibits their activity. Parasympathetic input to the colon has a prokinetic effect on colonic motility and represents the primary neural pathway through which defecation is regulated by the central nervous system.3
Colonic propulsion
Propulsion in the colon depends largely on mass movements, which are associated with inhibition of haustral segmentation and intestinal wall contractions. Large contractions of colonic smooth muscle cells result in increases in intraluminal pressure, termed high-amplitude propagated colonic contractions, which are the primary motor patterns associated with mass movements. The neurophysiological mechanisms underlying the generation of high-amplitude propagated colonic contractions are not fully understood. However, they can be observed in response to a high-calorie meal, upon awakening, and in response to chemical stimulation (for example, with stimulant laxatives such as bisacodyl); these mechanisms support the clinical recommendation to take advantage of the gastrocolic reflex after meals and upon waking to facilitate evacuation. High-amplitude propagated colonic contractions have been associated with the movement of colonic content and defecation, propagating from the cecum to the rectum, and imaging studies have demonstrated that more than 50% of colonic content can be evacuated during defecation.3
Retrograde propulsion
Colonic content also moves in a retrograde direction. Retrograde propulsion of the distal colon can occur after a meal and when defecation is withheld. Recent recordings from high-resolution colonic manometry (measurement of pressure changes reflecting contractions in the colon) have revealed a cyclic motor pattern propagated in a retrograde manner that originates at the rectosigmoid junction. This motor pattern increases after a meal and can be initiated by the delivery of stool or gas from the proximal colon, which may serve as a brake to prevent rectal filling. In support of this, the higher the frequency of retrograde phasic sigmoid contractile activity, the lower the number of defecatory episodes.
Subtypes of chronic constipation according to pathophysiological mechanism
Functional constipation can be classified into three types depending on its pathophysiological mechanism (Fig. 1): 1) normal-transit constipation, 2) dyssynergic defecation, and 3) slow-transit colonic constipation. Furthermore, these three types of chronic constipation show substantial overlap with one another and may present in combination in the same patient.
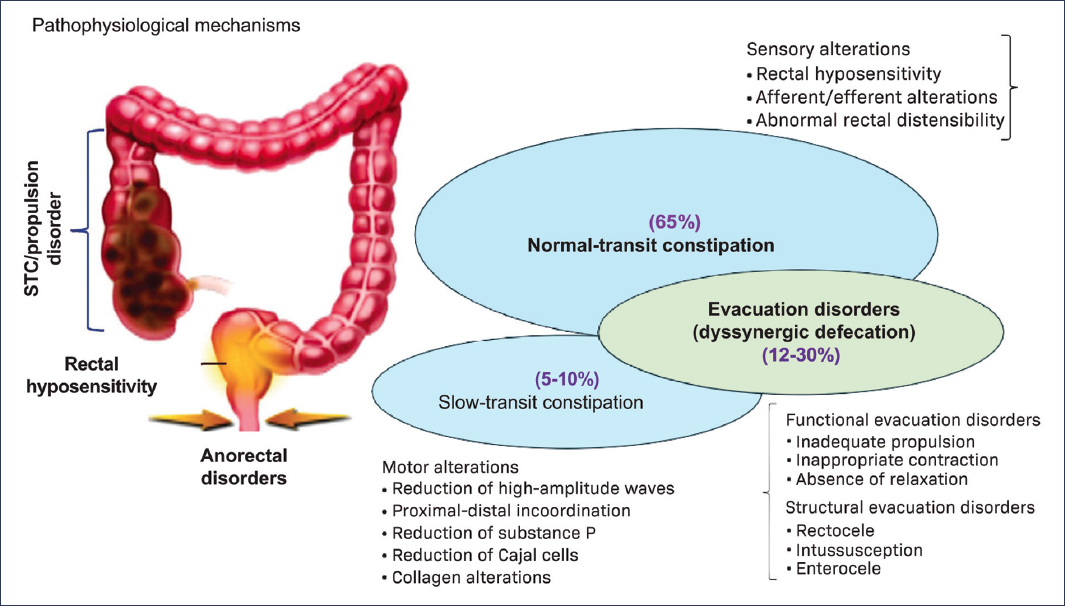
Figure 1. Main pathophysiological mechanisms associated with chronic constipation.4,8 NO: nitric oxide; STC: slow transit constipation; VIP: vasoactive intestinal peptide.
Normal-transit constipation
This is the largest group of patients with primary chronic constipation; in up to 65% of these patients, there is no evidence of slow colonic transit or dyssynergic defecation, and thus they are classified as having normal-transit constipation. The pathophysiology leading to chronic constipation in this group is unknown. Pain is the pivotal symptom, and the condition overlaps considerably with constipation-predominant irritable bowel syndrome. It has also been associated with alterations in rectal sensitivity (particularly hyposensitivity), which relates to a blunted or diminished perception of rectal distension; this can be explained by the fact that some patients do not experience the urge to defecate and, additionally, by alterations in the perception of stool frequency and consistency.1,3,4
Dyssynergic defecation
Evacuation of stool requires coordination between straining and relaxation of the pelvic floor muscles and anal sphincters. Incoordination between rectal pressure and sphincter relaxation (paradoxical contractions or failure of relaxation during straining) is common. Rectal evacuation disorders include functional anorectal disorders (e.g., dyssynergic defecation) or structural disorders (e.g., rectocele, descending perineum syndrome, rectal intussusception, or rectal prolapse). These disorders constitute the second most common type of chronic constipation. Dyssynergic defecation is the most prevalent subtype among rectal evacuation disorders. Most patients are unable to coordinate the abdominal, rectal, anal, and pelvic floor muscles during attempted defecation, and this lack of coordination manifests as a paradoxical anal contraction, inadequate anal relaxation, or impaired rectal or abdominal propulsive force. It is believed to be an acquired behavioral disorder of defecation. In two-thirds of adult patients, it results from poor toileting habits, painful defecation, obstetric or back injury, or gut-brain axis dysfunction. In the remaining third, the defecation process may not have been adequately learned during childhood, either due to behavioral problems or parent-child conflicts. Additionally, two-thirds of patients with dyssynergic defecation present with rectal hyposensitivity; approximately 60% of patients with dyssynergic defecation have secondary slow-transit constipation. Paradoxical anal contraction was originally considered an involuntary anal spasm during defecation. Body position, the sensation of stool, and stool characteristics influence defecation; even healthy individuals can demonstrate dyssynergia in the supine position despite having normal function and stool expulsion in the seated position.1–3
Slow-transit colonic constipation
One of the central mechanisms in the pathophysiology of chronic constipation is impaired colonic motility, particularly in the slow-transit constipation phenotype. Studies using high-resolution colonic manometry have demonstrated a significant reduction in the frequency, amplitude, and propagation of high-amplitude colonic contractions, as well as a loss of postprandial and circadian motor responses. These alterations lead to reduced propulsion of fecal content and prolongation of colonic transit time, especially in the proximal and transverse colon. Additionally, a relative increase in non-propulsive or even antiperistaltic motor patterns in the distal colon has been described, contributing to fecal retention. These abnormalities suggest a disruption in the integration of colonic peristaltic circuits, which are dependent on both the enteric nervous system and extrinsic autonomic modulation, resulting in an uncoordinated increase in distal colonic motor activity.4 Furthermore, alterations in the number of neurons in the myenteric plexuses expressing substance P (an excitatory neurotransmitter), the decreased production of inhibitory neurotransmitters such as nitric oxide and vasoactive intestinal peptide, and the reduction in the number of interstitial cells of Cajal responsible for the generation and propagation of colonic slow waves and neuromuscular coupling exhibit quantitative reduction and structural alterations in patients with slow-transit colonic constipation. Loss or dysfunction of these cells disrupts the synchronization of contractile activity and promotes ineffective motor patterns, directly contributing to the colonic hypomotility characteristic of slow-transit constipation.1,2
Gut microbiota, metabolites, and regulation of colonic motility
The gut microbiota constitutes a key modulator of the pathophysiology of chronic constipation through metabolic, neuroendocrine, and immune mechanisms. Experimental models have demonstrated that the microbiota can exert a causal effect on intestinal transit; however, in humans, the relationship is bidirectional, as slow transit promotes dysbiosis, establishing a vicious cycle between the luminal ecosystem and motor dysfunction.4 In patients with chronic constipation, reduced microbial diversity, a decrease in short-chain fatty acid-producing bacteria, and an increase in methanogenic microorganisms have been demonstrated – changes that are associated with slowing of colonic transit.1 Short-chain fatty acids, particularly butyrate, modulate colonic neuromuscular excitability, serotonin release, and postprandial motor response. The decrease in these metabolites contributes to the hypomotility and propulsive dysfunction observed in chronic constipation. The microbial metabolism of bile acids represents another relevant pathophysiological axis. Alterations in the conversion of primary to secondary bile acids reduce the activation of receptors such as FXR and TGR5, with a direct impact on colonic secretion and motility.1
Taken together, the gut microbiota acts as a transversal modulator capable of amplifying or attenuating pre-existing motor, sensory, and neuromuscular defects. Its role in the pathophysiology of chronic constipation reinforces the notion that this disorder cannot be understood solely from a neuromuscular perspective, but rather as the result of a dynamic interaction between the host and the luminal ecosystem.4
Low-grade inflammation and tissue remodeling
In subgroups of patients with chronic constipation, low-grade mucosal and submucosal inflammation has been identified, with mild immune infiltrates and changes in the extracellular matrix. These processes can lead to tissue remodeling, fibrosis, and altered colonic distensibility, thereby perpetuating motor dysfunction. This mechanism may explain the progression and refractoriness observed in some patients with long-standing chronic constipation.1 In surgical series and biopsies from patients with slow transit, findings of enteric neuropathy have been observed (reduction of neurons in the myenteric and submucosal plexuses), along with alterations in neurotransmission markers (e.g., decrease in neuronal nitric oxide synthase), submucosal or muscular fibrosis, and changes indicative of myopathy in selected cases. These data support the notion that in a subgroup of patients with functional constipation, the disorder may correspond to a true progressive enteroneuropathy or myopathy rather than a purely reversible dysfunction.5
Gut-brain axis alterations
The gut-brain axis plays a critical modulatory role in the pathophysiology of chronic constipation. Alterations in the central processing of visceral signals, psychological factors, and mood disorders can influence both intestinal perception and motility. Functional neuroimaging studies have demonstrated distinct brain activation patterns in patients with chronic constipation, suggesting aberrant central modulation of defecatory reflexes.1 Subgroups exist with altered rectal thresholds (hypo- or hypersensitivity) that affect the perception of urgency and the coordination of the defecatory reflex. Spinal afferent integration and cortical modulation can facilitate or inhibit motor responses, and abnormalities in central processing and psychological factors can perpetuate retention even with relatively preserved motility. Studies using the barostat and rectal distension testing have shown that rectal hypersensitivity is associated with greater symptom severity and evacuatory dysfunction.1
Immune and hormonal mechanisms
Although the etiology of slow-transit colonic constipation remains unclear, several pathophysiological features have been observed in these patients, and understanding continues to evolve. There is a marked female predominance, and a hormonal contribution to the etiology has been hypothesized. In colectomy specimens, an increase in progesterone receptors has been demonstrated, correlating with alterations in contractile and inhibitory G proteins.
In a small percentage of patients with gastrointestinal dysmotility, including slow-transit colonic constipation, autoantibodies have been detected, suggesting a possible autoimmune etiology in some cases.6
Pan-enteric and sensory alterations
Up to one-third of patients with slow-transit colonic constipation may present with gastric or small intestinal dysmotility, supporting a pan-enteric disorder in certain cases. Furthermore, the interplay between rectal distension (hyposensitivity) and inhibitory colonic feedback contributes to perpetuating transit delay.6
Fecal incontinence and chronic constipation
Fecal incontinence and chronic constipation are diagnosed as distinct problems, although many patients present with both. The phenotypic characteristics and underlying mechanisms of fecal incontinence combined with constipation are not well understood. Integrating a pathophysiological model, the evidence suggests a multifactorial mechanism whereby nerve injury or dysfunction (lumbosacral), along with rectal sensory alterations and changes in rectal distensibility, generates inadequate perception and motor response. This, combined with pelvic floor incoordination (dyssynergic defecation) and sphincter weakness or structural defects, results in incomplete emptying and delayed evacuatory transit. The interrelationship between hypersensitivity (urgency) and the inability to coordinate outflow explains the coexistence of constipation with episodes of fecal leakage in many patients.7
Conclusion
Chronic constipation is a pathophysiologically heterogeneous syndrome in which colonic dysfunction, alterations of the enteric nervous system (ENS) and interstitial cells of Cajal (ICC), evacuatory incoordination, luminal influences (microbiota and metabolites), and systemic factors interact to generate distinct phenotypes. Directed functional evaluation and the application of mechanism-specific therapies represent the current approach to optimizing outcomes in refractory patients and guiding future research.
Funding
The authors declare that they received no funding for this study.
Conflicts of interest
The authors declare no conflicts of interest.
Ethical considerations
Protection of persons and animals. The authors declare that no experiments were performed on humans or animals for this study.
Confidentiality, informed consent, and ethical approval. The study does not involve personal data, medical records, or human biological samples, and therefore does not require ethical approval. The SAGER guidelines do not apply.
Statement on the use of artificial intelligence. The authors declare that no type of generative artificial intelligence was used for the drafting or creation of content in this manuscript.
